
Ebola disease outbreak in the Democratic Republic of the Congo
This page is updated every weekday. It was last updated on 8 October at 16:25.
On 7 October 2026, the Democratic Republic of the Congo (DRC) reported a total of 8 728 confirmed cases, including 4 205 related deaths (from data up until 6 October). A total of 1 066 patients are hospitalised in isolation. This represents an increase of 63 new confirmed cases and 27 deaths since the previous report on 6 October (reporting data up until 5 October). The 63 new cases have been reported from Ituri (33 cases), and North Kivu (30 cases). Among the individuals who tested positive for Bundibugyo virus, 2 269 have recovered. In total, 82% of identified case contacts are under follow-up in the affected provinces.
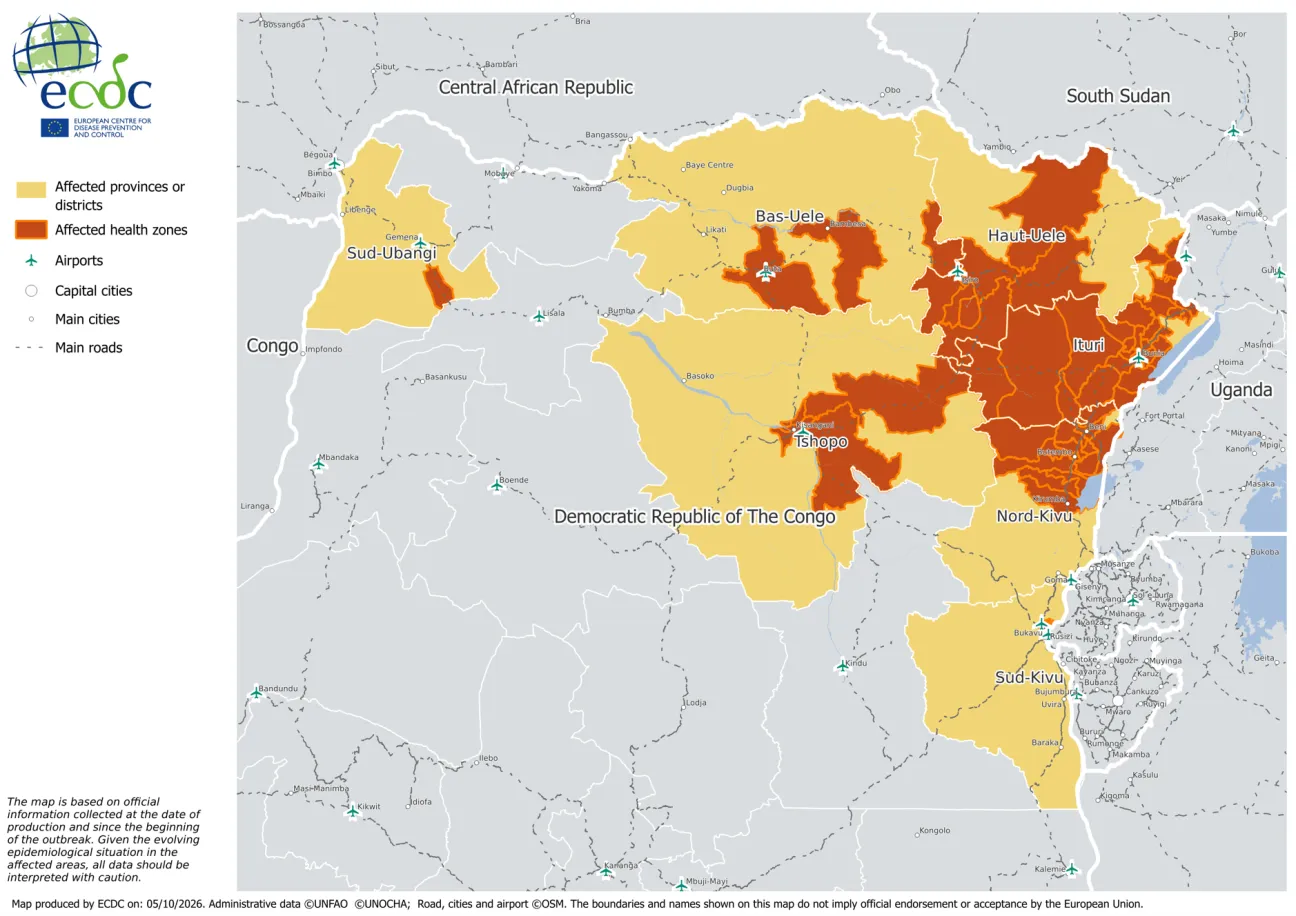
Ituri province remains the most affected, with 6 513 cases, including 3 007 deaths, reported from 28 of 36 health zones. In North Kivu, 1 785 cases, including 1 021 deaths, have been reported from 17 of 34 health zones. In South Kivu, three cases, including one death, have been reported from one of 34 health zones. In Haut-Uélé, 364 cases, including 153 deaths, have been reported from seven of 13 health zones. In Tshopo, 51 cases, including 18 deaths, have been reported from seven of 23 health zones. In Bas-Uélé, 10 cases, including four deaths, have been reported from three of 11 health zones. In Sud Ubangi, two cases and one death have been reported from one of 16 health zones. Overall, 64 of 167 health zones are currently affected across the seven provinces.
Data reported by DRC on confirmed cases and deaths are under continuous review and harmonisation.
On 6 October 2026, Kenya's Cabinet Secretary for Health announced the country's first confirmed imported Ebola virus disease case. The patient, a Kenyan citizen who had been residing in the DRC, reportedly travelled from the DRC through Uganda and arrived in Nairobi on 3 October. The patient subsequently died. According to the Minister, 28 contacts, including family members and healthcare workers, have been identified and quarantined.
In Uganda, a total of 20 cases were reported between May and June 2026 by the Ministry of Health. On 25 August, WHO declared the end of the outbreak following 42 days without a new confirmed case being reported.
Monitoring medically evacuated and imported cases to/in Europe
A healthcare worker based in DRC who tested positive for Bundibugyo virus on 29 September was medically evacuated to the Netherlands to receive specialised care. The patient was admitted to the high-level isolation unit at Leiden University Medical Center on 1 October.
In May 2026, there was an imported case in a US citizen who was medically evacuated to Germany for treatment, and on 24 June 2026 a further imported case was reported in France by the Ministry of Health. Both cases were imported from areas affected by the ongoing outbreak in DRC. On 10 July 2026, the US CDC reported that a US citizen working for a humanitarian organisation in DRC had tested positive for Bundibugyo virus. The patient was medically evacuated to Germany on 13 July 2026. On 21 July, the United Kingdom Ministry of Health reported that a UK resident who had been treating patients with Ebola in the DRC was evacuated and had been isolated in a London hospital.
According to ECDC modelling calculations, the risk of importation into the EU/EEA from the outbreak area remains very low. While sporadic importations cannot be excluded, the probability of multiple independent importations is very low, even in a pessimistic scenario whereby incidence continues to rise in the affected regions. These results are consistent with ECDC’s June.
ECDC’s modelling focuses on the general population of the Ituri and North Kivu provinces in DRC and does not take into account healthcare workers and other professionals returning from the affected region. Although these groups have a substantially greater risk of exposure, they are subject to infection control measures and monitoring protocols. As a result, the probability of infection and of travel may differ considerably from that of the general population.
The risk of importation depends on outbreak size, travel behaviour, and travel volume. Due to limited information, assumptions are made on all three factors based on the best available information.
A weekly update on this outbreak is available in the Communicable disease threats report.
Areas in DRC affected by the ongoing Ebola disease outbreak
Read the threat assessment

Questions and answers

Basic facts about the current Ebola disease outbreak in the Democratic Republic of Congo and Uganda.

Questions and answers about the current outbreak of Ebola disease for healthcare professionals in Europe.
Resources and guidance

Guidance, training materials and operational resources for public health authorities, healthcare professionals and transport operators.

Laboratory guidance, diagnostic protocols and technical resources for laboratories.

Communication materials and resources for the public, healthcare professionals, airlines and airport staff.


