Key facts
- As of 15 June 2026, a total of 782 confirmed cases, including 181 confirmed related deaths (an increase of 106 new cases and 45 new deaths since the previous update) have been reported in the Democratic Republic of the Congo (Ituri, North Kivu and South Kivu Provinces); a total of 19 confirmed cases, including two deaths, have been reported in Uganda.
- On 17 May 2026, the World Health Organization declared that the Ebola disease outbreak due to Bundibugyo virus constitutes a Public Health Emergency of International Concern, and on 18 May 2026 Africa CDC declared a Public Health Emergency of Continental Security.
- Given all the available information and uncertainties about this outbreak, the likelihood of infection for people from the EU/EEA living in or travelling to affected areas is estimated to be low. For people living in the EU/EEA, the likelihood of infection is estimated to be very low, given the very low likelihood of importation and secondary transmission. This assessment will be reviewed as further information becomes available.
- ECDC is monitoring the outbreak through epidemic intelligence activities and liaising with partners.
Overview
Latest epidemiological information
Democratic Republic of the Congo
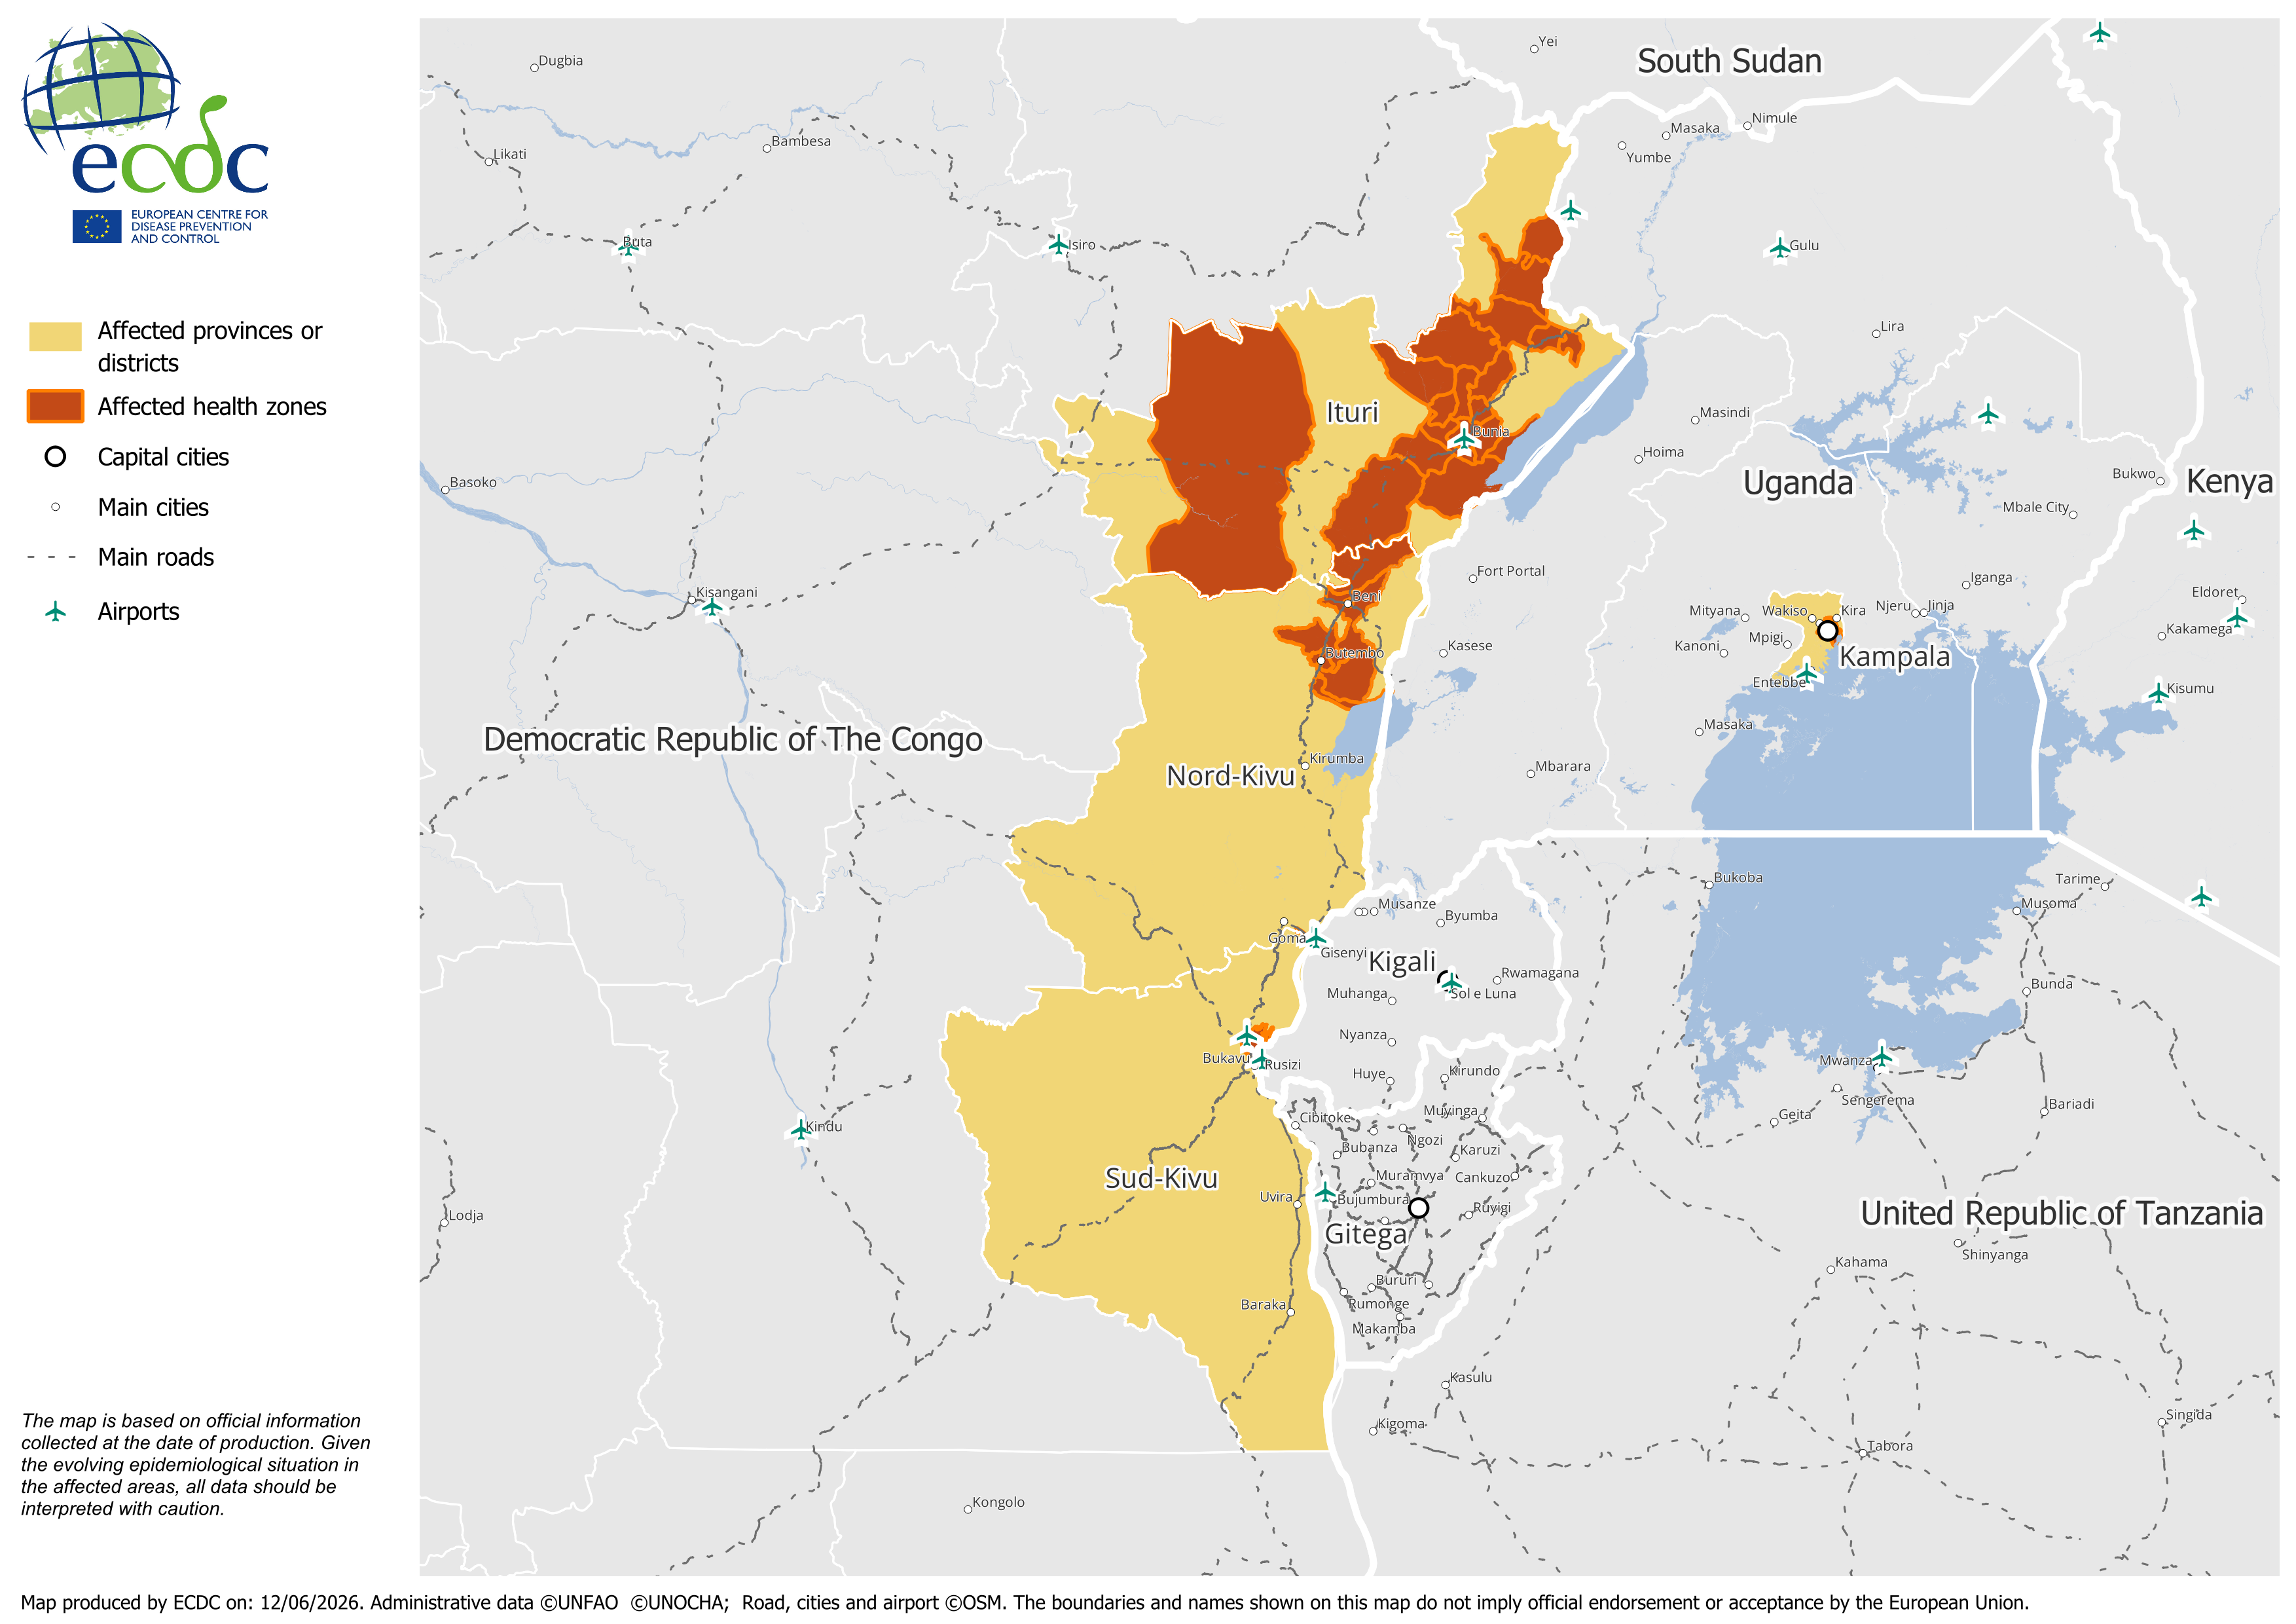
According to the official report published on 14 June 2026 (data as of 13 June), a total of 782 confirmed cases, including 181 confirmed related deaths, have been reported in the Democratic Republic of the Congo (DRC). Since the previous Communicable Disease Threats Report published on 12 June 2026, (data as of 11 June), an additional 106 new cases and 45 new deaths have been reported. Among the confirmed cases, 717 cases (including 146 deaths) have been reported in the Ituri province, 62 cases (including 34 deaths) in North Kivu, and three cases (including one death) in South Kivu. In addition, 359 patients were reported to have been hospitalised in isolation. Forty individuals who previously tested positive for Ebola disease have recovered and 56.5% of identified contacts are under follow-up.
Within the three affected provinces, 31/104 health zones are currently affected, including 20/36 in Ituri, 10/34 in North Kivu, and 1/34 in South Kivu. Two new affected health zones were reported on 13 June, of which one in Ituri (Nia-Nia, 1 case) and one in North Kivu (Mabalako, 1 case). Of the 717 confirmed cases reported in Ituri, 94 have not been assigned to a health zone.
According to the World Health Organization (WHO), 16 of the confirmed cases reported as of 13 June involved health and care workers.
Uganda
As of 14 June, a total of 19 confirmed cases, including two deaths, have been reported by the Ministry of Health in Uganda. Five individuals have recovered. The last confirmed cases were reported on 5 June by the Ministry of Health and no new cases have been reported since.
Among the confirmed cases, 14 had travel links to DRC and five were associated with local transmission events, according to health officials. Of nine cases with known geographical information, eight were reported in Kampala and one was reported in Wakiso (a district that neighbours Kampala).
One case reported by Uganda had travel history to the United Arab Emirates (UAE), arriving on 24 May (Media reports on 1 June 2026, WHO media briefing on 3 June 2026, WHO DON 8 June 2026). According to WHO, as of 8 June, no cases of Ebola disease have been reported in the UAE; public health measures including risk assessment activities, contact tracing and follow-up, and strengthened preparedness measures at points of entry have been implemented in coordination between WHO, UAE and international partners.
Several symptomatic travellers from affected areas have been tested in EU/EEA and non-EU/EEA countries, all of whom have tested negative so far.
Summary
On 15 May 2026, Africa CDC reported an outbreak of Ebola disease in Ituri Province, DRC (Africa CDC Calls Urgent Regional Coordination Meeting Following Ebola Virus Disease Outbreak in Ituri, 15 May 2026, Africa CDC Special Briefing on Ebola Virus Disease Outbreak Status, 16 May 2026). Laboratory analysis at the Institut National de Recherche Biomedicale of DRC identified Bundibugyo virus (Democratic Republic of the Congo confirms new Ebola outbreak, WHO scales up support | WHO AFRO, 15 May 2026).
Clusters of community deaths have been reported, including deaths among healthcare workers in DRC (Epidemic of Ebola Disease caused by Bundibugyo virus in the Democratic Republic of the Congo and Uganda determined a public health emergency of international concern, 17 May 2026, Ebola disease caused by Bundibugyo virus, Democratic Republic of the Congo (The) & Uganda).
The Ministry of Health of DRC reported that the index case was a nurse (age unknown) who died in a healthcare facility in Bunia (capital of Ituri Province). The case presented with fever, bleeding, vomiting and weakness (Ministère de la Santé RDC Declaration of Ebola Outbreak 15 May 2025). However, the outbreak is likely to have started many weeks before, given the number of cases and the geographical spread.
On 18 May 2026, a US citizen working in healthcare in the affected areas tested positive and was transferred to Germany, together with six high-risk contacts (US CDC Update on Ebola Outbreak, 18 May 2026, Serge News and Updates, 18 May 2026). The American doctor subsequently recovered well and was discharged from the hospital in Berlin where he was treated (Ebola patient discharged from Charite hospital in Berlin in good health, 6 June 2026). Another contact of US nationality was transferred to Czechia (US CDC Transcript -19 May 2026).
The first case reported in Uganda was travel related and the patient later died (Democratic Republic of the Congo confirms new Ebola outbreak, WHO scales up support | WHO AFRO, 15 May 2026, Epidemic of Ebola Disease caused by Bundibugyo virus in the Democratic Republic of the Congo and Uganda determined a public health emergency of international concern, 17 May 2026). Health authorities reported that 14 confirmed cases in Uganda had travel links to DRC. Additional cases were identified following contact tracing activities. Uganda has postponed a large religious event (Martyr's day) that normally takes place on 3 June and has suspended cross-border transport activities (Government of Uganda on X: 21 May 2025).
Genomes from DRC and Uganda have been published and preliminary analysis shows distinct sequences from the previous outbreaks (Virological Ebolavirus/Bundibugyo ebolavirus, 18 May 2026).
Information regarding transmission chains and affected population groups is currently limited, partly due to the complex context of insecurity and humanitarian challenges in the affected areas. According to WHO, neighbouring countries sharing land borders with DRC are considered at high risk of further spread due to population mobility, trade and travel links, and uncertainty about the transmission chains. The outbreak may also be larger than currently detected. There are also concerns related to this outbreak because it is caused by Bundibugyo virus, rather than the more commonly detected Zaire ebolavirus. Unlike Zaire ebolavirus, there are currently no licensed vaccines or specific treatments for Bundibugyo virus disease.
Given the information available, the complicated context and the uncertainties regarding epidemiological information, WHO declared a Public Health Emergency of International Concern on 17 May 2026 (Epidemic of Ebola Disease caused by Bundibugyo virus in the Democratic Republic of the Congo and Uganda determined a public health emergency of international concern, 17 May 2026). On 18 May 2026, Africa CDC declared the outbreak a Public Health Emergency of Continental Security (Africa CDC Declares the Ongoing Bundibugyo Ebola Outbreak a Public Health Emergency of Continental Security – Africa CDC, 18 May 2026). On 5 June, WHO and Africa CDC launched a joint continental preparedness and response plan to support African countries in the response to the ongoing outbreak.
This is the 17th Ebola disease outbreak reported in DRC. The most recent prior outbreak occurred in 2025 in Kasai Province due to Ebola virus species Orthoebolavirus zairense (WHO DON Ebola virus disease – Democratic Republic of the Congo, 5 September 2025). In Ituri province specifically, Ebola disease due to Ebola virus Orthoebolavirus zairense was last documented during the 2018–2020 outbreak. This outbreak was declared on 1 August 2018 following reports of laboratory-confirmed cases in North Kivu province. Investigations identified cases in Ituri and North Kivu with symptom onset from May 2018. The outbreak also spread to South Kivu. Between 1 August 2018 and 25 June 2020, when the outbreak was declared over, a total of 3 470 cases were reported, including 3 317 confirmed cases and 153 probable cases. At the time, WHO declared the outbreak a Public Health Emergency of International Concern (Disease Outbreak News Ebola virus disease – Democratic Republic of the Congo, 26 June 2020, Medical countermeasures during the 2018 Ebola virus disease outbreak in the North Kivu and Ituri Provinces of the Democratic Republic of the Congo: a rapid genomic assessment - ScienceDirect).
Bundibugyo virus was first reported in 2007 in Bundibugyo district in Uganda, during an outbreak. The most recent outbreak due to Bundibugyo virus was in 2012 in DRC (Uganda: Ebola outbreak press statement - 20 Dec 2007 - Uganda | ReliefWeb, WHO | Ebola outbreak in Democratic Republic of Congo, 12 August 2012).
Travel restrictions
Enhanced control and screening protocols have been activated by authorities in several countries to limit the risk of viral spread.
Exit screening has been implemented in DRC, Uganda and South Sudan. In DRC, points of entry (PoE) and points of control (PoC) have been activated at key locations, including airports, road checkpoints and towns or local transit points, such as Nizi and Irumu (Ituri), Mudzibala (Bunia), Dele and Chai (Rwampara). Bunia airport in the Ituri province was temporarily closed on 23 May and re-opened on 2 June with the implementation of health screening measures. Commercial flights to and from Bunia airport have been temporarily suspended again as of 6 June, as part of health security arrangements in response to the Ebola outbreak, as also reported by media.
The Rwandan Ministry of Health has reinforced health screening and vigilance at land points of entry along the border with DRC. Enhanced entry control measures have been implemented at Kigali International Airport for inbound travellers to Rwanda (Rwanda Ministry of Health, 22 May on X).
Several countries have also implemented entry restrictions and health screening for individuals travelling from high-risk countries, including the US, Canada, Tunisia, Thailand, Mauritius and the Bahamas (Ebola Update - Travel Measures and Ongoing Monitoring).
ECDC assessment
Considering the remaining gaps in the epidemiological information and limited follow-up of contacts, it is expected that the outbreak is much larger than is currently being reported – not only in terms of the number of affected cases, but also its geographical extent.
Given all the available information and uncertainties surrounding this outbreak, the likelihood of infection for people from the EU/EEA living in or travelling to affected areas is estimated to be low. For people living in the EU/EEA, the likelihood of infection is estimated to be very low, given the very low likelihood of importation and secondary transmission. The likelihood of Bundibugyo virus affecting the donor population for substances of human origin in the context of this outbreak is currently assessed as very low. This assessment will be reviewed as further information becomes available.
Exit screening in affected countries, including symptom checks and exposure assessment, is important as it contributes to risk reduction by identifying symptomatic travellers before they board flights to prevent them travelling while symptomatic. Exit screening also helps dissuade people with symptoms from travelling and enhances public and stakeholder confidence. However, it cannot fully prevent exportation of cases, because the absence of symptoms at departure does not exclude subsequent onset of disease.
ECDC considers that screening of returning travellers from affected areas (DRC, Uganda) would not be effective in preventing introduction to Europe. This consideration is based on the lessons learned and results of the large EVD outbreak in West Africa between 2013 and 2016, where tens of thousands of cases were reported, transmission was ongoing in large urban centres, and hundreds of EU/EEA humanitarian and military personnel were deployed to the affected areas. Screening incoming travellers is time- and resource-consuming and will not effectively identify people with the infection. Priority should instead be given to providing travellers with clear information on symptoms, routes of transmission, and what to do if symptoms develop after arrival in the EU/EEA.
Detailed assessment of the event can be found in the ECDC Threat Assessment Brief published on 21 May 2026 (Threat assessment brief: Ebola disease outbreak caused by Bundibugyo virus – Democratic Republic of the Congo and Uganda – 2026).
Actions
ECDC continues to monitor the outbreak through its epidemic intelligence activities to provide epidemiological updates, situational awareness and risk assessment for the EU/EEA.
Since 19 May 2026, the EU Health Task Force, in collaboration with DG ECHO, DG INTPA and GOARN, is deploying ECDC experts to Africa CDC headquarters in Addis Ababa.
ECDC is actively liaising with key partners, including Africa CDC, the European Commission and WHO, to provide further support through the EU Health Task Force in response to this outbreak.
ECDC is regularly re-evaluating the situation as new information becomes available and continues to provide epidemiological updates and scientific advice on its website. A Threat Assessment Brief and Laboratory guidance and resources on the Ebola outbreak were published on 21 May 2026 and 27 May 2026, respectively.