
Ebola disease outbreak in the Democratic Republic of the Congo
This page is updated every weekday. It was last updated on 15 October at 13:30.
As of 13 October 2026, the Democratic Republic of the Congo (DRC) reported a total of 9 144 confirmed cases, including 4 410 related deaths (from data up until 12 October). A total of 899 patients are hospitalised in isolation. On 12 October, 79 new confirmed cases and 11 deaths were reported. The 79 new cases have been reported from Ituri (40 cases), North Kivu (27 cases), and Haut-Uele (8 cases). Among the individuals who tested positive for Bundibugyo virus, 2 418 have recovered. In total, 77.6% of identified case contacts are under follow-up in the affected provinces.
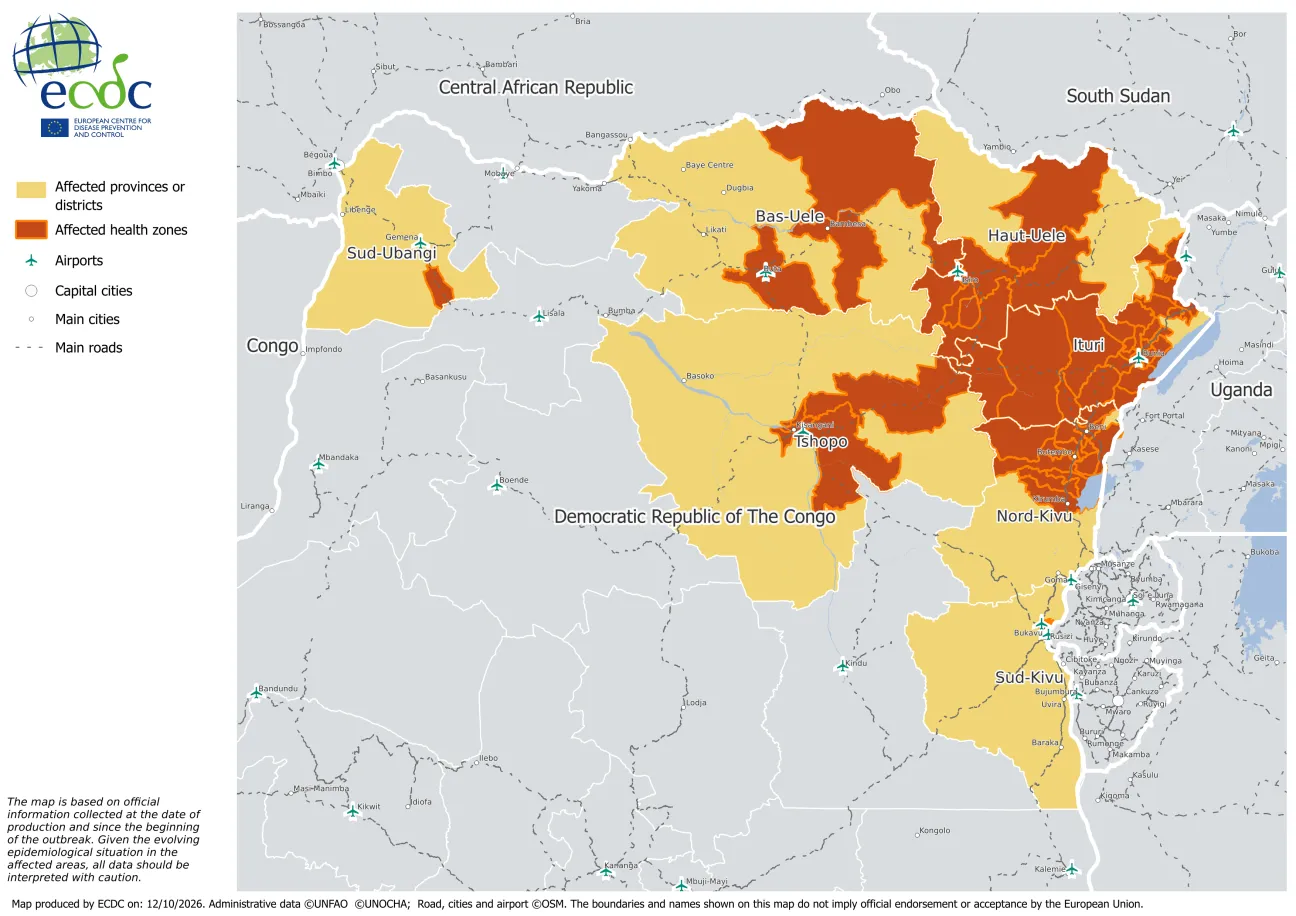
Ituri province remains the most affected, with 6 734 cases, including 3 177 deaths, reported from 28 of 36 health zones. In North Kivu, 1 938 cases, including 1 102 deaths, have been reported from 17 of 34 health zones. In South Kivu, three cases, including one death, have been reported from one of 34 health zones. In Haut-Uélé, 391 cases, including 163 deaths, have been reported from seven of 13 health zones. In Tshopo, 63 cases, including 22 deaths, have been reported from seven of 23 health zones. In Bas-Uélé, 13 cases, including four deaths, have been reported from four of 11 health zones. In Sud Ubangi, two cases and one death have been reported from one of 16 health zones. Overall, 65 of 167 health zones are currently affected across the seven provinces.
Data reported by DRC on confirmed cases and deaths are under continuous review and harmonisation.
On 6 October 2026, Kenya’s Cabinet Secretary for Health announced the country’s first confirmed imported Ebola virus disease case. The patient, a Kenyan citizen who had been residing in DRC, reportedly travelled from DRC to Kenya, via Uganda, on 3 October. The patient subsequently died. On 11 October, the Cabinet Secretary for Health stated that 108 of the patient zero’s 122 listed contacts are in quarantine and have not developed symptoms.
In Uganda, a total of 20 cases were reported between May and June 2026 by the Ministry of Health. On 25 August, WHO declared the end of the outbreak, following 42 days without a new confirmed case being reported.
Monitoring cases that were medically evacuated or imported to Europe
A healthcare worker based in DRC who tested positive for Bundibugyo virus on 29 September was medically evacuated to the Netherlands to receive specialised care. The patient was admitted to the high-level isolation unit at Leiden University Medical Center on 1 October.
In May 2026, there was an imported case in a US citizen who was medically evacuated to Germany for treatment, and on 24 June 2026 a further imported case was reported in France by the Ministry of Health. Both cases were imported from areas affected by the ongoing outbreak in DRC. On 10 July 2026, the US CDC reported that a US citizen working for a humanitarian organisation in DRC had tested positive for Bundibugyo virus. The patient was medically evacuated to Germany on 13 July 2026. On 21 July, the United Kingdom Ministry of Health reported that a UK resident who had been treating patients with Ebola in DRC was evacuated and had been isolated in a London hospital.
According to ECDC modelling calculations, the risk of importation into the EU/EEA from the outbreak areas remains very low. While sporadic importations cannot be excluded, the probability of multiple independent importations is very low, even in a pessimistic scenario whereby incidence continues to rise in the affected regions. These results are consistent with ECDC’s previous assessment: ‘Estimation of the importation risk of Bundibugyo virus into the EU/EEA in June 2026’.
ECDC’s modelling focuses on the general population of the Ituri and North Kivu provinces in DRC and does not take into account healthcare workers or other professionals returning from the affected region. Although people working in healthcare in the region have a substantially greater risk of exposure, they must comply with infection prevention and control measures and monitoring protocols. As a result, the probability that these individuals will acquire an infection and then travel may differ considerably from that of the general population.
The risk of importation into the EU/EEA also depends on outbreak size, travel behaviour and travel volume. Due to limited information, assumptions are made on all three of these factors, based on the best available information.
A weekly update on this outbreak is available in the Communicable disease threats report.
Areas in DRC affected by the ongoing Ebola disease outbreak
Read the threat assessment

Questions and answers

Basic facts about the current Ebola disease outbreak in the Democratic Republic of Congo and Uganda.

Questions and answers about the current outbreak of Ebola disease for healthcare professionals in Europe.
Resources and guidance

Guidance, training materials and operational resources for public health authorities, healthcare professionals and transport operators.

Laboratory guidance, diagnostic protocols and technical resources for laboratories.

Communication materials and resources for the public, healthcare professionals, airlines and airport staff.


